


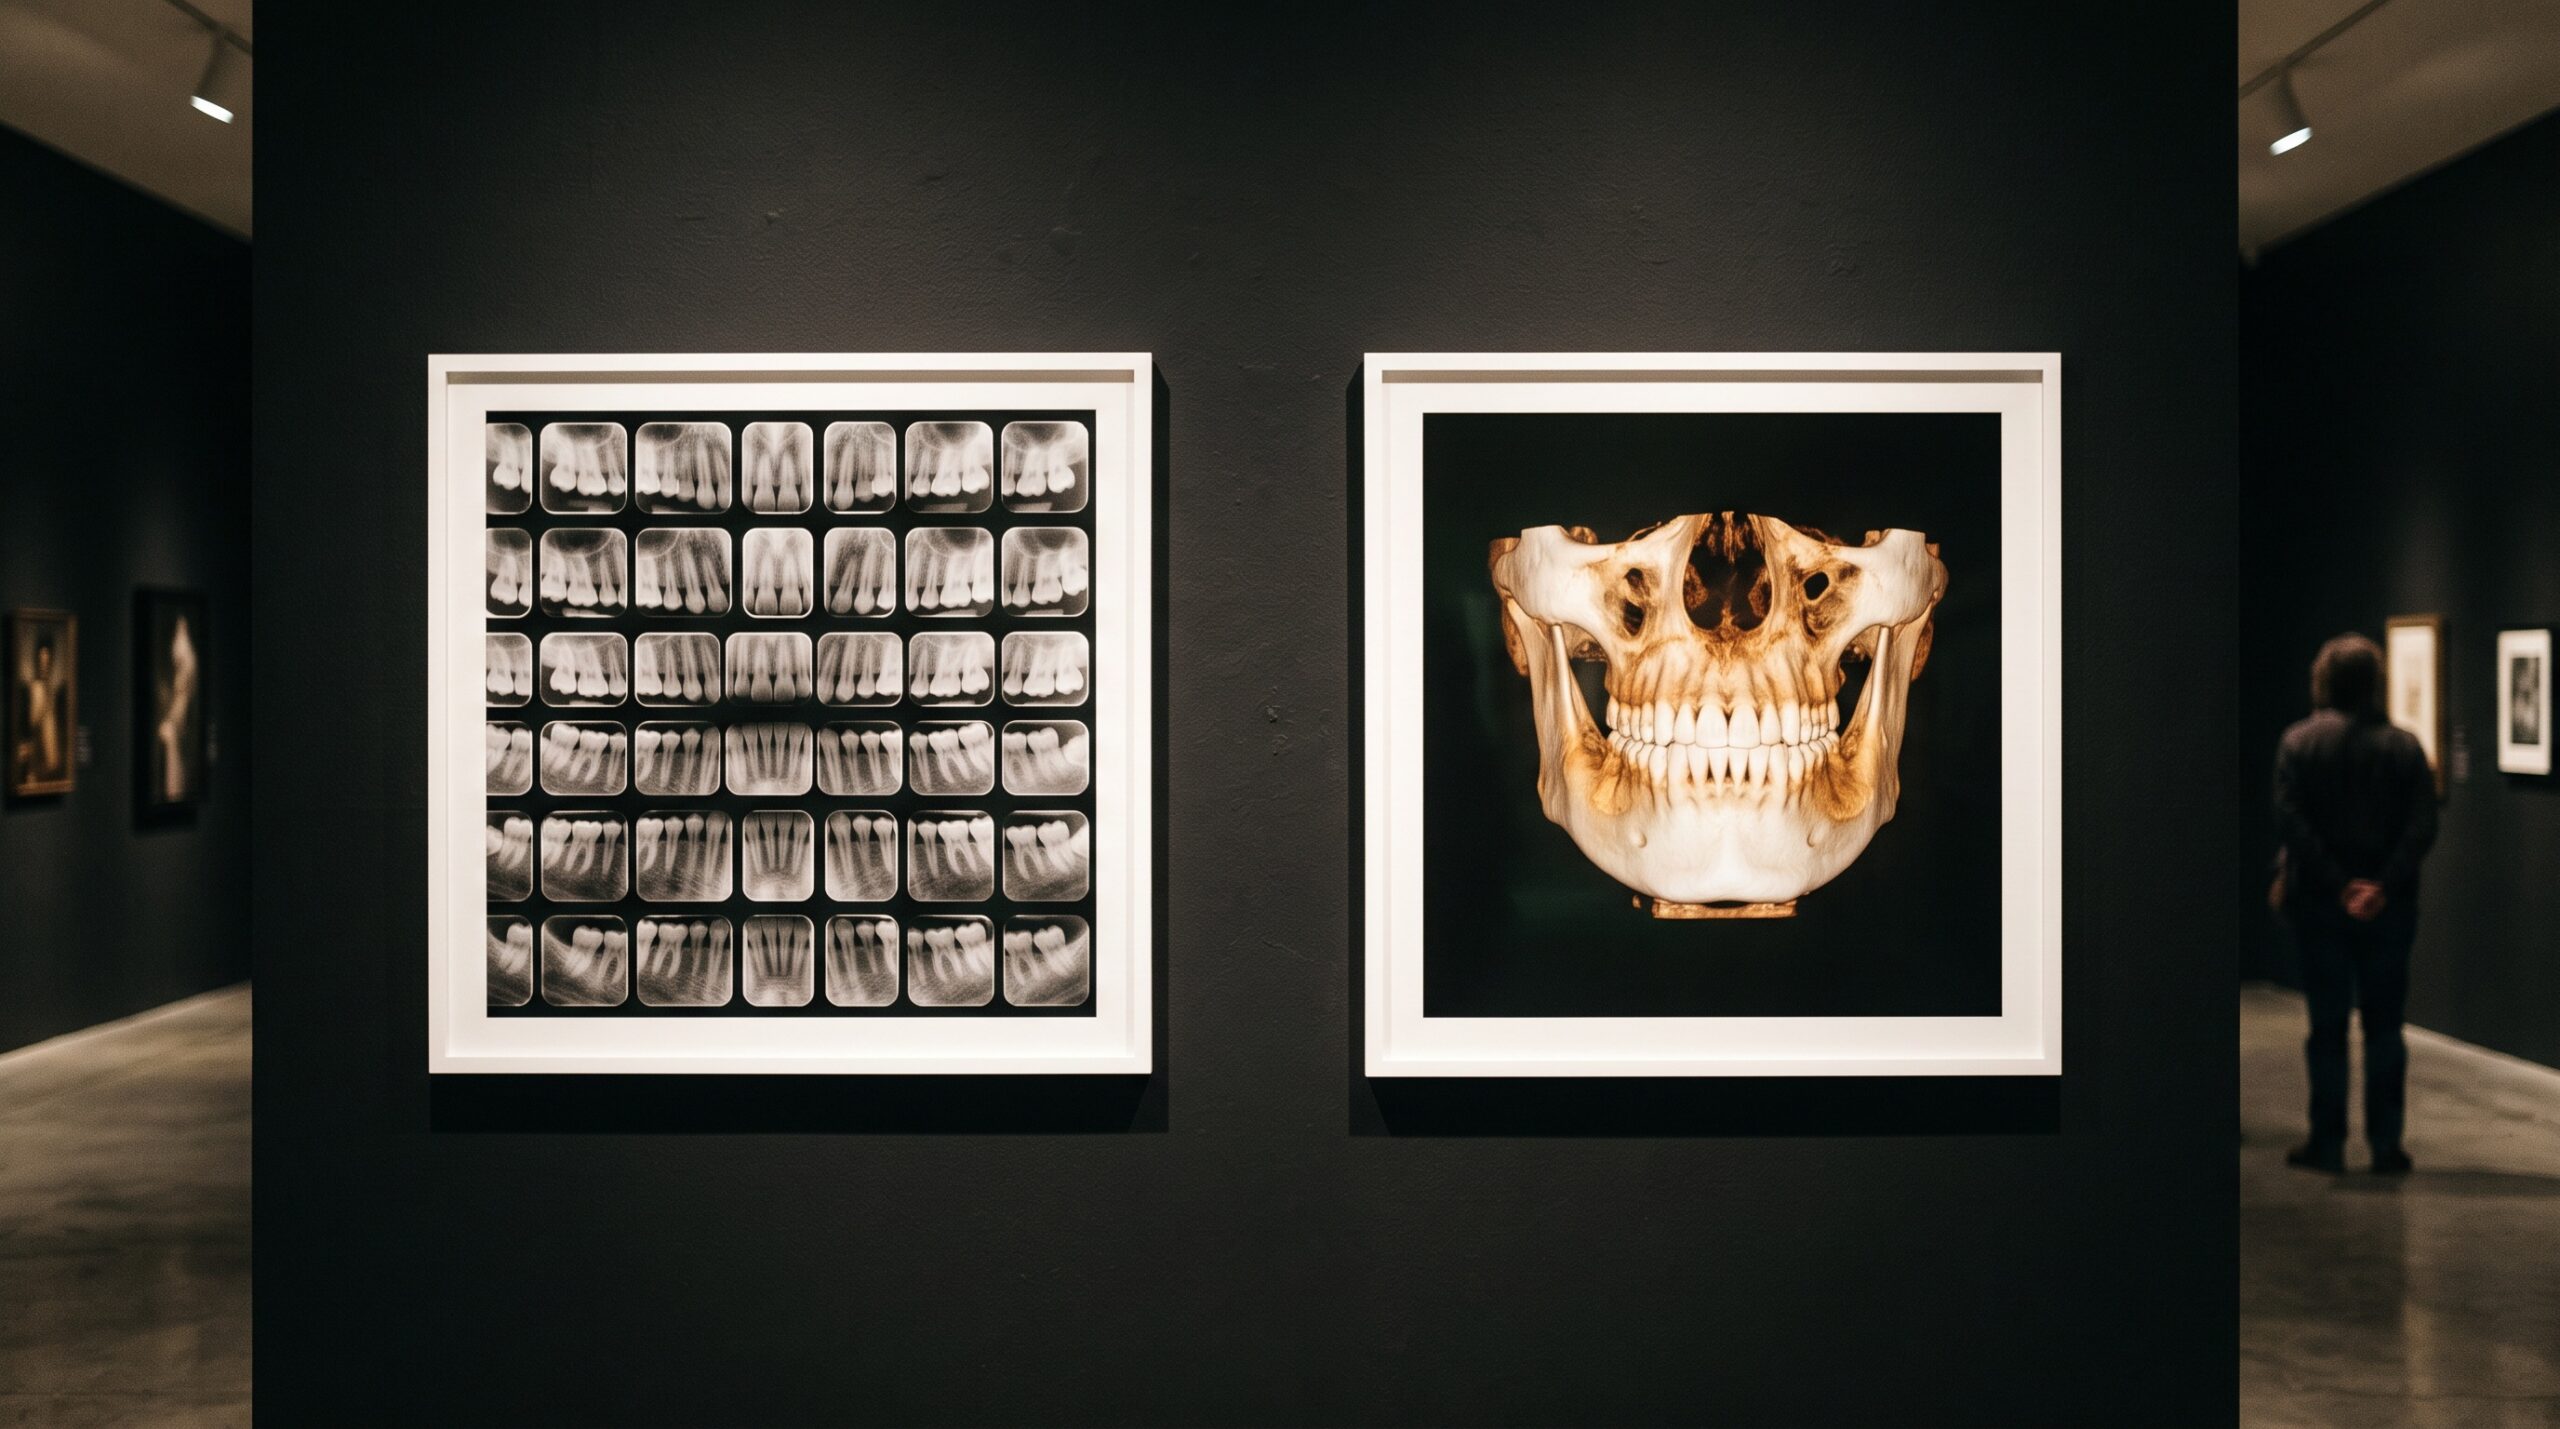
October 26, 2026 Full-Mouth Series or Cone-Beam CT? Reading the Diagnostic Question Before You Choose the Modality
A full-mouth series and a cone-beam scan are often spoken of as if one were simply a better, newer version of the other — as though three dimensions must always trump two. A gallerist knows better. A detailed etching and a sculpture are not competing attempts at the same thing; they are different instruments, each able to show what the other cannot. So it is here. The intraoral full-mouth series (the FMX) and cone-beam computed tomography (CBCT) answer different questions, carry different costs, and belong to different moments in a patient’s care. The skill worth cultivating is not a preference for one over the other but the ability to read the diagnostic question clearly enough to know which instrument it is actually asking for.
The short answer, for the reader who wants it before the detail: reach for the full-mouth series when the question is about the fine surface and structure of teeth and the bone immediately around them — interproximal caries, periodontal bone levels, periapical status. Reach for CBCT when the question is genuinely three-dimensional — the position of an impacted tooth, the course of the inferior alveolar nerve, the volume of bone available for an implant, a fracture or lesion whose geometry a flat image can only hint at. Everything below is the craft of telling those two kinds of question apart.
At a Glance: Two Instruments, Compared
| Criterion | Full-Mouth Series (FMX) | Cone-Beam CT (CBCT) |
|---|---|---|
| Dimension | Two-dimensional projection; overlapping structures are superimposed | Three-dimensional volume; structures separated in space and reconstructable in any plane |
| Spatial resolution | Very high at the tooth surface; excels at fine detail and early interproximal caries | High but typically coarser than intraoral film; detail depends on voxel size and field of view |
| Best-answered questions | Caries, periodontal bone level, periapical pathology, restoration margins, routine survey | Impactions, nerve mapping, implant site planning, complex endodontics, fractures, bony lesions, airway and TMJ |
| Radiation dose | Low; a complete series remains a modest effective dose | Meaningfully higher, varying widely with field of view and protocol; small-FOV, low-dose settings narrow the gap |
| Field of view | Fixed to the dental arches, tile by tile | Selectable — from a single tooth to the full maxillofacial region; a dose decision in itself |
| Typical role | The baseline survey and the recall workhorse | The problem-solving study, ordered for a specific spatial question |
What the Full-Mouth Series Does Better
The FMX is a mosaic of high-resolution windows, each small film placed close against the teeth to capture crown, root, and surrounding bone with exquisite surface fidelity. For the questions that fill most operatory hours — is there decay forming between these two teeth, has the bone level around this molar changed since last year, is there a shadow at this root apex — the two-dimensional survey is not merely adequate; it is frequently superior. Its resolution at the tooth surface outpaces that of most cone-beam protocols, and early interproximal lesions in particular are read with a clarity that a volumetric scan, with its coarser voxels and its averaging, can blur. This fidelity is a product of the whole imaging chain, right down to the X-ray source behind every intraoral exposure and the sensor that receives it. The FMX is also the lighter study by far in dose terms, which is precisely why it remains the sensible baseline and the recall workhorse rather than a relic awaiting replacement.
What Only the Volume Can Show
CBCT earns its place the moment the question stops being what and becomes where. A flat radiograph collapses depth: two structures at different distances from the sensor land on the same point of the image, and the clinician is left to infer a third dimension that the picture does not actually contain. For an impacted canine whose position relative to the roots of its neighbours determines the surgical approach, for an implant site whose buccolingual bone width decides whether a fixture will fit, for an endodontic case with an extra canal hiding behind another, that inference is not good enough. The cone-beam volume separates what the projection superimposes. It does not give a sharper photograph; it gives a different kind of object — sliceable, rotatable, measurable — and for genuinely spatial problems it is transformative. The same volumetric capability now extends into motion and function, as when a still CBCT is fused with live jaw-motion tracking to study the bite as it actually moves.
The Dose Is Part of the Picture
No comparison of these two instruments is honest without the scale on which every exposure is weighed: diagnostic benefit on one pan, radiation dose on the other. A complete full-mouth series carries a modest effective dose. A cone-beam study carries a higher one — how much higher depends enormously on the field of view and the protocol, with a small-FOV, low-dose acquisition of a single region sitting far closer to the 2D study than a large craniofacial volume does. The radiosensitive tissues of the head and neck, and the longer lifetimes of younger patients, mean this difference is not academic. The field of view is therefore not a technical afterthought but a clinical and ethical choice: capture the smallest volume that answers the question, at the lowest dose that will still answer it. Here the hardware is quietly helping, as photon-counting detectors now entering maxillofacial imaging push more diagnostic information out of each delivered dose.
Reading the Question Before the Exposure
This is where the two instruments resolve into a single discipline. The recent ADA patient-selection guidance made the order of operations explicit: examine the patient, review the history, consult the prior images, and only then decide whether a new exposure — and which kind — will genuinely change management. The choice between FMX and CBCT is simply that principle applied with care. A cone-beam scan ordered reflexively for a question a bitewing would have answered is dose spent without benefit; a flat survey asked to resolve a three-dimensional surgical problem is a false economy that invites a repeat study. Neither instrument is the default. The default is the question, read clearly, in the light of the ADA’s guidance on imaging in moderation — and the modality chosen as its answer.
Future Developments
The boundary between these two instruments will grow both sharper and, in a sense, more porous. Dose-efficient detectors and smarter low-dose protocols will keep lowering the cost of the volumetric study, narrowing the gap that today makes the FMX the obvious lighter choice. Artificial intelligence will increasingly read both — flagging interproximal caries on the 2D survey, segmenting nerve canals and measuring bone on the 3D volume — and may in time help answer the selection question itself, suggesting from the clinical findings which instrument a case truly requires. But the underlying craft will not change. The gallery of the future will still hold both the detailed survey and the luminous volume, and the measure of the clinician will remain what it is now: not the instrument owned, but the question read — and the quiet confidence to choose the exposure the diagnosis actually asked for, and no more.
Sources & further reading:
- Full-mouth series x-rays vs. cone-beam computed tomography: What dental hygienists need to know (DrBicuspid)
- New Recommendations Confirm Dental X-Rays Most Effectively Used in Moderation (ADA)
- CBCT: radiation risk or diagnosis risk? (Nature, BDJ)
No Comments